6 Answers sorted by
420
Tl;dr: I think we can vaguely guess a 1.5-2x risk reduction from a third shot, maybe pushing 2-2.5x if you get it close to 6 months after the first; for those with less immunity after two shots, it might be more like expected 3-6x, though it’s unclear if one can discern who these are. If you do get a third shot, you should definitely try to get a different kind, as others have said, though unclear if you want to sacrifice efficacy for this.
---------
First, to establish an expected effect size, how good are the first two shots? The first Pfizer/Moderna takes you to about 80% protection, or a 4/5 risk reduction. The second takes you to 95% efficacy, a 4x risk reduction. To compare, Delta variant takes Pfizer from 95% back to 80, so is a 4x risk increase. So most likely, the third vaccine is not going to be as efficient as the second vaccine. So we expect less than a 4x effect; realistically, maybe I expect something like 2x at the outset since secondary boosters are common in immunology and third boosters aren't. I wouldn't be that surprised at seeing 3x or 1.25x though. (Note that this is all about transmission, for a shot of the same type as your first two; probably slightly stronger effect than this in mortality, and mixed vaccinations I'll get to at the end).
There's no released data, so we have to get creative fast. The best empirical evidence I know of comes from this study on how much vaccinations boost your neutralizing antibody (NAb) titers after already having COVID. (NAbs are by no means all of your immunity, but they’ve been shown to correlate surprisingly well with vaccine effectiveness. Hilariously, there are nonetheless papers claiming we have some evidence that NAbs can CAUSE infections to be worse—while this may be true, all I can do is plead for them to make a better case that this isn’t bog-standard Treatments Correlated with Harm.)
Anyways, this study shows limited effect from a second Pfizer vaccine dose if the patient had already contracted COVID! It’s useful because very roughly speaking, getting COVID gives similar titers as a vaccine dose—and COVID plus one dose is similar to two doses, so looking at COVID plus two doses is a good approximation for a third dose. This gives us some limited evidence that a third dose won’t be that effective.
Notably though, it did significantly increase the titers of the least-protected! This seems like a decent reason to get a third vaccine if you are vulnerable. To put very rough numbers on it, my guess is that for the vulnerable it would cut risk by a factor of 3, whereas the group as a whole only gets a factor of about 1.5.
- Calculation: Getting a second dose cuts risk by 4 as we’ve already said; on this graph the first to second shot gives a jump in titers by about 3 logs, whereas it looks like the vulnerable have their titers go up about 2.5 logs from the third shot, so I’ll give this a ~3-fold reduction. The group as a whole only goes up about 1 log on the third-dose-equivalent, which is maybe a factor of 1.5 protection. Both of these figures match well with our original bound of finding less than a 4x average reduction, and quite well with my prior of about 2x!
As a second creative line of evidence, could we figure out anything from the claims from Pfizer that their third dose increases neutralizing antibody (NAb) titers by by 5-10x?
Is 5-10x a lot? Unfortunately, a major hurdle is that every vaccine appears to measure NAbs using different assays, with no translation to efficacy. I really hope I’m mistaken here, because otherwise it seems like every report of increasing titers by X-fold is almost completely meaningless, e.g. this otherwise-nice comparison. But I don’t think I am.
I tried going through other Pfizer studies to see if maybe they at least used a single assay across the board. One Pfizer study says a factor of 1.5 difference in unnamed geometric titers for a strain meant roughly nothing. Another shows about a 4x factor in log2PRNT50 difference between Delta and wild-type, which corresponds to about a 4x decreased efficacy as we know from elsewhere. But this can’t be the same as the above-stated titer, because that would mean a 5-10x reduced risk from a third shot, which is way higher than our bounds. It’s possible that if we escape the log though, this becomes a 16x titer difference for 4x risk reduction, which is at least in the ballpark and would imply a 2x risk reduction from the third shot. I think this is on shaky ground though and I don’t place much stock at all in it, even if it happens to pop out the magic number.
-----
A very important thing here that a few people mentioned: combating waning vaccine efficacy is important. Many studies show this effect, but I’ll cite my favorite that I linked earlier. It predicts about a 2x risk increase (or effectiveness decrease) over 6 months. Another study shows variable waning from natural infection that roughly accords with this, at least insofar as NAb titers from this or similar papers can be interpreted.
There are two questions here: first, would a third vaccine reverse this waning effect? There aren’t data to confirm this yet, but surely the answer is yes—this is how other vaccine boosters work, and all theory points to this being the case. The second question is whether the third vaccine’s natural effect, as described early to be ~~1.5x normally or ~~3x for the vulnerable, would fully stack on top of a waning-reversal. I think the answer is probably no, but with partial effect, closer to fully stacking than not. Part of this answer comes from the idea that the longer you wait between doses, the more effective they are. In total then, I expect a booster after 3 months to give you about 2x risk reduction, and 4x for the vulnerable.
Last, I completely agree with the other people bringing up that getting a different third dose seems better than the same (though the same shot seems still worth it for many, as above). I wish I had gotten my second dose of a different kind—this is significantly because of “original antigenic sin”, the tendency to get antibody lock-in toward whatever strains you experience early. I expect different vaccines as boosters will help somewhat with this problem, though I really can hardly speculate quantitatively about this—all I’ll say is I would be unsurprised to see that taking this strategy with the right vaccine might get you 4x instead of 2x from a third shot. (However, you’d need both an effective vaccine and for it to be substantially different than the first one or two—and I don’t know if Moderna/Pfizer fit that bill. Perhaps I can research this in the future, or how much effectiveness to sacrifice for difference, though it sounds hard and by default I won’t since I don’t think it’s all that decision-relevant.)
Two last thoughts: if Elizabeth is right in the comments about a possible low limit for mRNA vaccines, that’s a major downside. If it weren’t for that, it would almost surely be worth it to get a 3rd shot for most people by the calculus, since Delta is growing so fast and has so little morbidity for the vaccinated that there isn’t much incentive to keep it out of young and healthy circles. (Cf about 4 days of expected lost life from Delta while vaccinated, and getting a third shot would save you 2 expected days at a cost of two days lightly sick. But if there's much cost in the vein of what Elizabeth mentions, that washes out.)
*
210EDITED: Connor's comment below landed directly in a place where I was ignorant and I've updated to think the right answer is "defer to him on the details of immunology until I read a lot more".
I feel like what I wrote was basically adequately hedged given my ignorance, and maybe it is interested to read for having some of the picture, but not all of the picture, but if you're just saving your attention for super high value things you can probably just skip it? I get kind of rant-y towards the end about the lack of a proper public health system. Maybe if you like the rant-y bit this is still worth reading for that?
...
My current personal mechanistic model is that for "a given challenge" (that occurs in a window roughly 6-21 days large, with variation between people and also between challenges for the same person in different states of health), people either have a germinal center response, or not.
If not, then on a second attempt they might have a response again, or not. This is "in general". I've seen studies where they did really good followup with a population for a measles vaccine, and some patients managed to play along with followup 5 times, and only the 6th vaccine caused their immune system to finally begin testing positive for the desired antibodies.
However, my current personal mechanistic model has huge error bars, and numerous asterisks, with warnings about how immunology is a blacker art that computer security, because it basically IS computer security, but for programs written in nucleic acid that are billions of years old, with millions of new revisions spammed into existence every second by a mad god. I can't read the code (at least not most of it, and not easily). I just expect it to contain devilish tricks because: it would be surprising if it didn't.
Under the simple "response or not" model, the reason they did "two tries without bothering to check in between for a response" for the current Pfizer/Moderna design is that this "double tap" protocol ups the official "chance of having the response from the one official protocol" and basically jukes their numbers, so they can brag about a 90% efficacy "if you do it right" and this makes the narrative and the medical protocols and everything simpler.
If I was rich enough to have a private doctor (I'm not, and I don't even have "a doctor" as such because of moves and paperwork and dealing with insurance paperwork constantly being so so so exhausting) then I could totally see just paying "one competent personal doctor" to acquire and administer one vaccine dose, test for response, then doing another dose only if the antibody test is negative... but also doing a third if the antibody test after the second didn't show that it worked, and so on.
However, under the "response or not" model this binary response is for a specific epitope (or epitopeS if several antibodies form for different surface bits of different proteins... I'm not personally clear on how the immune system picks exactly what folded protein surface part(s) to pick as a target, or why) and so if you have DIFFERENT vaccines that target DIFFERENT surface patches on the same set of proteins (or variants of proteins) then for a specific later challenge by an environmental exposure probably the best fitting antibody for that exposure reacts the strongest and leads charge by the immune system to fight off the invading virus particles and their initial first couple generations of viral babies.
My current working model might be wrong. If it is right, then the best vaccines would target lots of different epitopes selected from numerous possible genetic variants and we would generate and ship them in maybe close to realtime, as a sort of "human culture and institution mediated meta immune system".
This is how a properly designed public health system would actually work. But the US does not have a public health system basically? It just has a pharmaceutical and medical licensing monopoly maintenance and legal challenge immunization system, that prevents incumbents in the medical industry from being competed into low margins and high consumer health surpluses :-(
If our country was well run, we would already have a delta booster designed and available that could trigger the formation of these new kinds of antibodies, and the reason we don't is because the government is "either evil or incompetent" and the private industry isn't allowed to innovate around this barrier to technologically solving technologically solvable problems. ("FDA delenda est", but that's neither here not there.)
(Maaaaybe someone HAS already designed such boosters, but the FDA and/or CDC threatened them with angry looks and being put on some kind of professional blacklist if they ever admitted this in public on the second go-around because the PR was so bad for them when it came out that the first mRNA vaccine was designed in early 2020?)
Basically, my model is that RaDVaC or other novel vaccine designs COULD improve your response to VARIANTS by increasing the breadth of covid epitopes that your body can recognize and respond to, but that if a given vaccine design triggered a response in you already then another one is unlikely to help much more...
...however I have genuine model uncertainty. Maybe a second exposure causes the specific form of specific immune responses to somehow be stronger or different in a way that I've never seen a clean and clear explication of? Some anecdotal evidence suggests that double-dosed people are safer than single-dosed people, but I've never seen anyone report anything like this with a coherent followup about how or why such anecdotes might occur more (or less) in "different worlds" where (1) single-dosed people are less likely to have had a germinal response at all vs (2) the second dose materially changes the nature of the immune response.
I'm interested in learning a better model, if my model is wrong.
Another thing to point out is that having more antibodies is called "being allergic to things" when the thing you have antibodies for something that isn't actually bad. And it is called an "autoimmune disease" when the antibodies recognize something that naturally is already part of you. Acquiring new antibodies is not totally risk free. All biology is half black magic and full of exceptions because evolution is deep and twisty. Please please please be careful!
If you want to give me the $1000 for this writeup, please give it to johnswentworth instead.
Huh, I'm pretty surprised by this model. Why do you think it's correct?
Here's an image of some measure of people's antibody responses from page 9 of this paper, where the first set of points is people's response 5-6 wks after dose 1, and the second set of points is people's response 2-3 wks after dose 2.
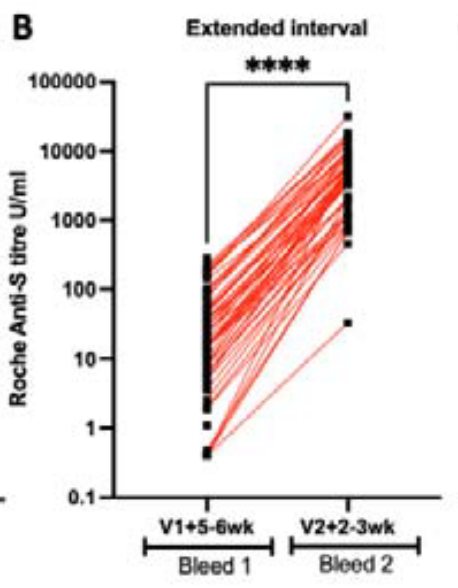
It looks like people who get an antibody response to the first dose still get a much improved response from a second dose. And there's no sign of a bimodal responses to any of the doses. Is that consistent with your model?
Also, the way vaccines can protect from severe disease without protecting from infection seems to suggest that there's more than a binary question of response/not-response.
150
According to one expert, the immune system essentially makes bets on how often it will face a given virus and how the virus will mutate in the future:
https://science.sciencemag.org/content/372/6549/1392
By that logic, being challenged more often means that the immune system should have a stronger and longer-lasting response:
The immune system treats any new exposure—be it infection or vaccination—with a cost-benefit threat analysis for the magnitude of immunological memory to generate and maintain. There are resource-commitment decisions: more cells and more protein throughout the body, potentially for decades. Although all of the calculus involved in these immunological cost-benefit analyses is not understood, a long-standing rule of thumb is that repeated exposures are recognized as an increased threat. Hence the success of vaccine regimens split into two or three immunizations.
The response becomes even stronger when challenging the immune system with different versions of the virus, in particular a vaccine and the virus itself (same link).
Heightened response to repeated exposure is clearly at play in hybrid immunity, but it is not so simple, because the magnitude of the response to the second exposure (vaccination after infection) was much larger than after the second dose of vaccine in uninfected individuals. [...] Overall, hybrid immunity to SARS-CoV-2 appears to be impressively potent.
For SARS-CoV-2 this leads to a 25-100x stronger antibody response. It also comes with enhanced neutralizing breadth, and therefore likely some protection against future variants.
Based on this, the article above recommends combining different vaccine modalities such as mRNA (Pfizer, Moderna) and vector (AZ) (see also here).
Lastly, your question may be hard to answer without data, if we extrapolate from a similar question where the answer seems hard to predict in advance:
Additionally, the response to the second vaccine dose was minimal for previously infected persons, indicating an immunity plateau that is not simple to predict.
90
Depending on when you got your second mRNA dose, the Israeli data suggests there is significant vaccine decline in vaccine efficacy after 3 months (see https://www.gov.il/BlobFolder/reports/vaccine-efficacy-safety-follow-up-committee/he/files_publications_corona_two-dose-vaccination-data.pdf ) This does not of course indicate whether a third dose would restore efficacy (presumably by reigniting the immune response in some way) - I suspect it would, however. No need for prize money if relevant - just resharing a link that was already in Forbes https://www.forbes.com/sites/roberthart/2021/07/23/pfizer-shot-just-39-effective-against-delta-infection-but-largely-prevents-severe-illness-israel-study-suggests/?sh=ca1146c584f1
10
It might be worth posting this question to Metaculus to see what the crowd-consensus view is there. I'd post a question myself there, but I'm not sure I have enough expertise to define the question and resolution properly (but it seems like you or others might).
-180
My guess is that you have generated your own hypothesis (namely, more than two doses will work better than 2 will). I almost always leave medical hypothesis generation to the medical experts with the result that my job is to choose among the hypotheses and to tailor my choice to my situation. Of course I consider hypotheses by contrarians and alternative health-care providers, which number in the high dozens or hundreds of hypotheses for Covid.
(Experts have proposed a 3rd shot, but that would be a shot of a new vaccine, not one currently being given to people.)
UPDATE: the bounty has now been awarded as follows:
===
Since I got vaccinated I’ve started working in-person, going to restaurants, travelling and whatever. But the delta variant might change this risk calculation. Some of the same buzz that got covid right early on, the first time around, is now buzzing about delta potentially being very bad.
So I’m exploring ways of responding to that. This time around I’d rather stand up and fight than lock myself in a house for a year. And so this question explores one possible approach.
There’s evidence that two vaccine doses are more effective than one (though there might be much higher diminishing returns than is commonly acknowledged). I’ve also heard that past infection confers marginal immunity even in the presence of vaccination. Further, as far as I understand, the 2-dose schedule for many vaccines is more “a common thing that we happened to test in the big trials” rather than “the dose level at which marginal benefit = marginal risk”. (And giving your population more than two doses is probably much harder logistically.)
Hence: getting more than the standard 1-2 vaccine doses might be a way to protect against delta.
I live in California, and we currently seem to have a large vaccine surplus. I heard a vague rumour about a friend basically just walking into a pharmacy and getting a 3rd shot. There’s also RADVAC, which you can make yourself.
So, if there is supply... how worthwhile is it to get more vaccine doses? Should you get a 3rd, 4th, … or even more? How does getting a further dose of the same vaccine compare to getting the first dose of a different vaccine?
I’m posting a bounty of $1000 for answers that change my mind on this question (maybe increasing to many times that if this proves valuable).
The ideal thing I want would be a graph with the x-axis showing # doses, and the y-axis reduction-vs-control of the following four parameters:
(Answers are of course impacted by the combinatorial search space of dose spacing / dose number / dose size / vaccine type / various demographics, but I won’t make any special restrictions here for now)
I will pay at least $1000 for answers that help me get clarity on this, split at my full discretion in proportion to how useful I find the answers. I’ll pay out the bounty on a rolling basis as answers come in; there is no deadline. In case this proves fruitful and there seems to be useful marginal work, it’s possible I will increase the bounty a lot (i.e. up to many thousands of dollars), or reach out to work with some answerers as contractors.